Access.
Use a lateral corridor anterior to the psoas, appropriate to the treated level and patient anatomy.

Vertebral Body Osteotomy
VBO®VBO restores foraminal height within a single vertebral body through an anterior-to-psoas lateral approach. Bone screws and a lateral plate secure the near side, and Vertiwedge®’s deployable staple secures the far side, all through the same access, without disc resection or interference. Vertiwedge is available in a wide range of sizes and lordotic and coronal angulations.
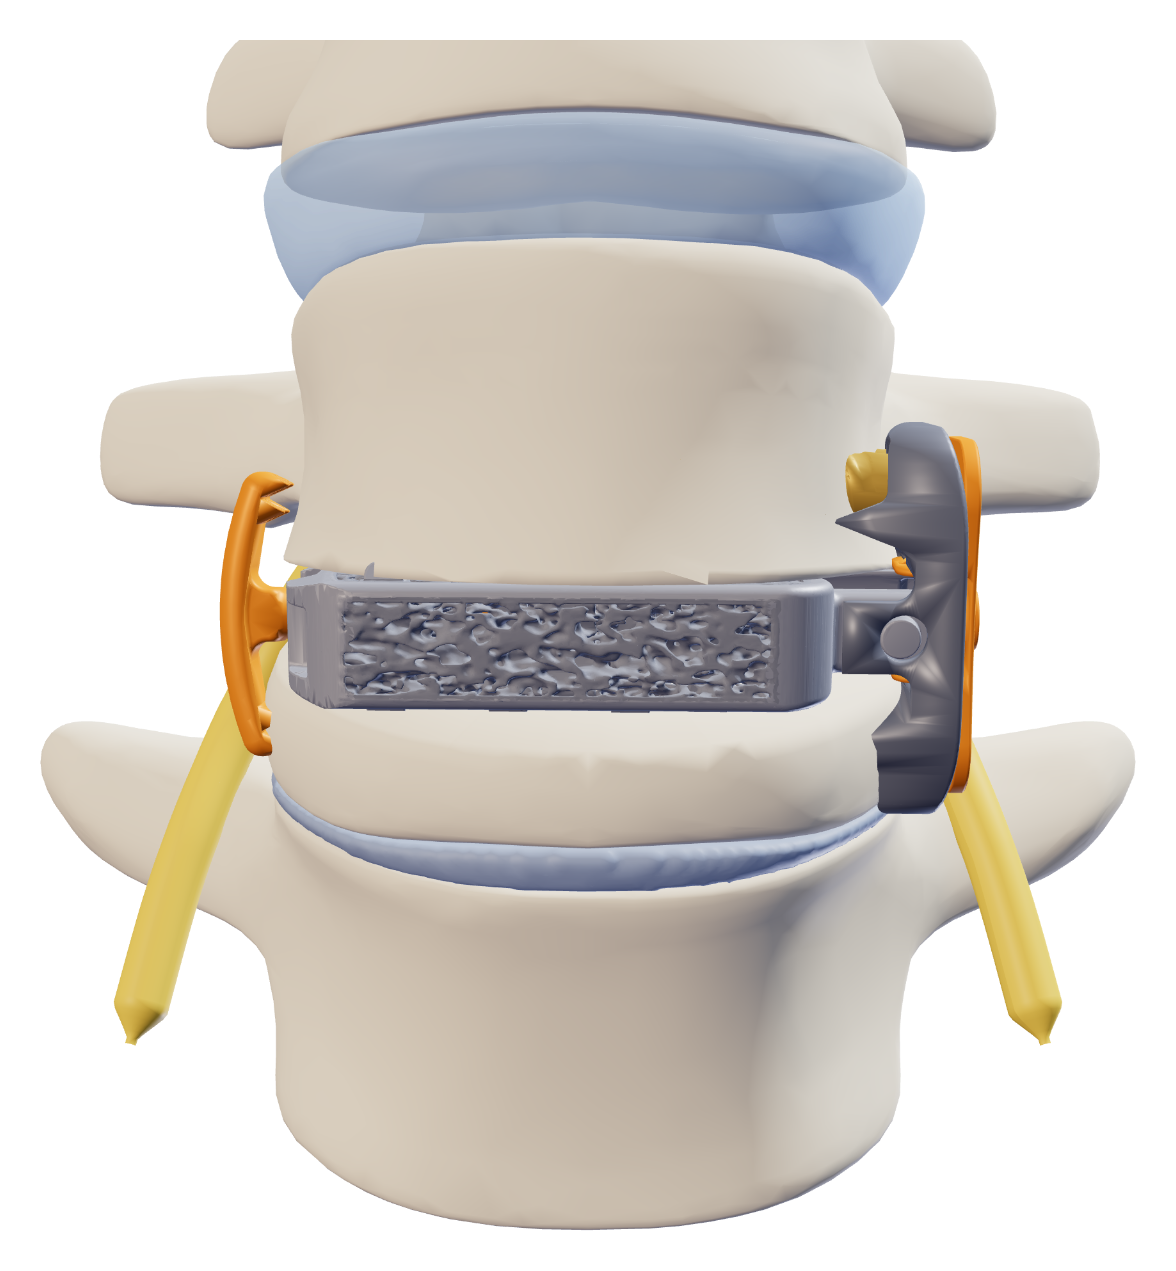
How VBO compares
Direct decompression preserves motion but doesn’t restore height or address alignment. Interbody fusion does both, but joins two vertebrae across the disc. VBO is designed to restore height and offer alignment options while preserving motion.
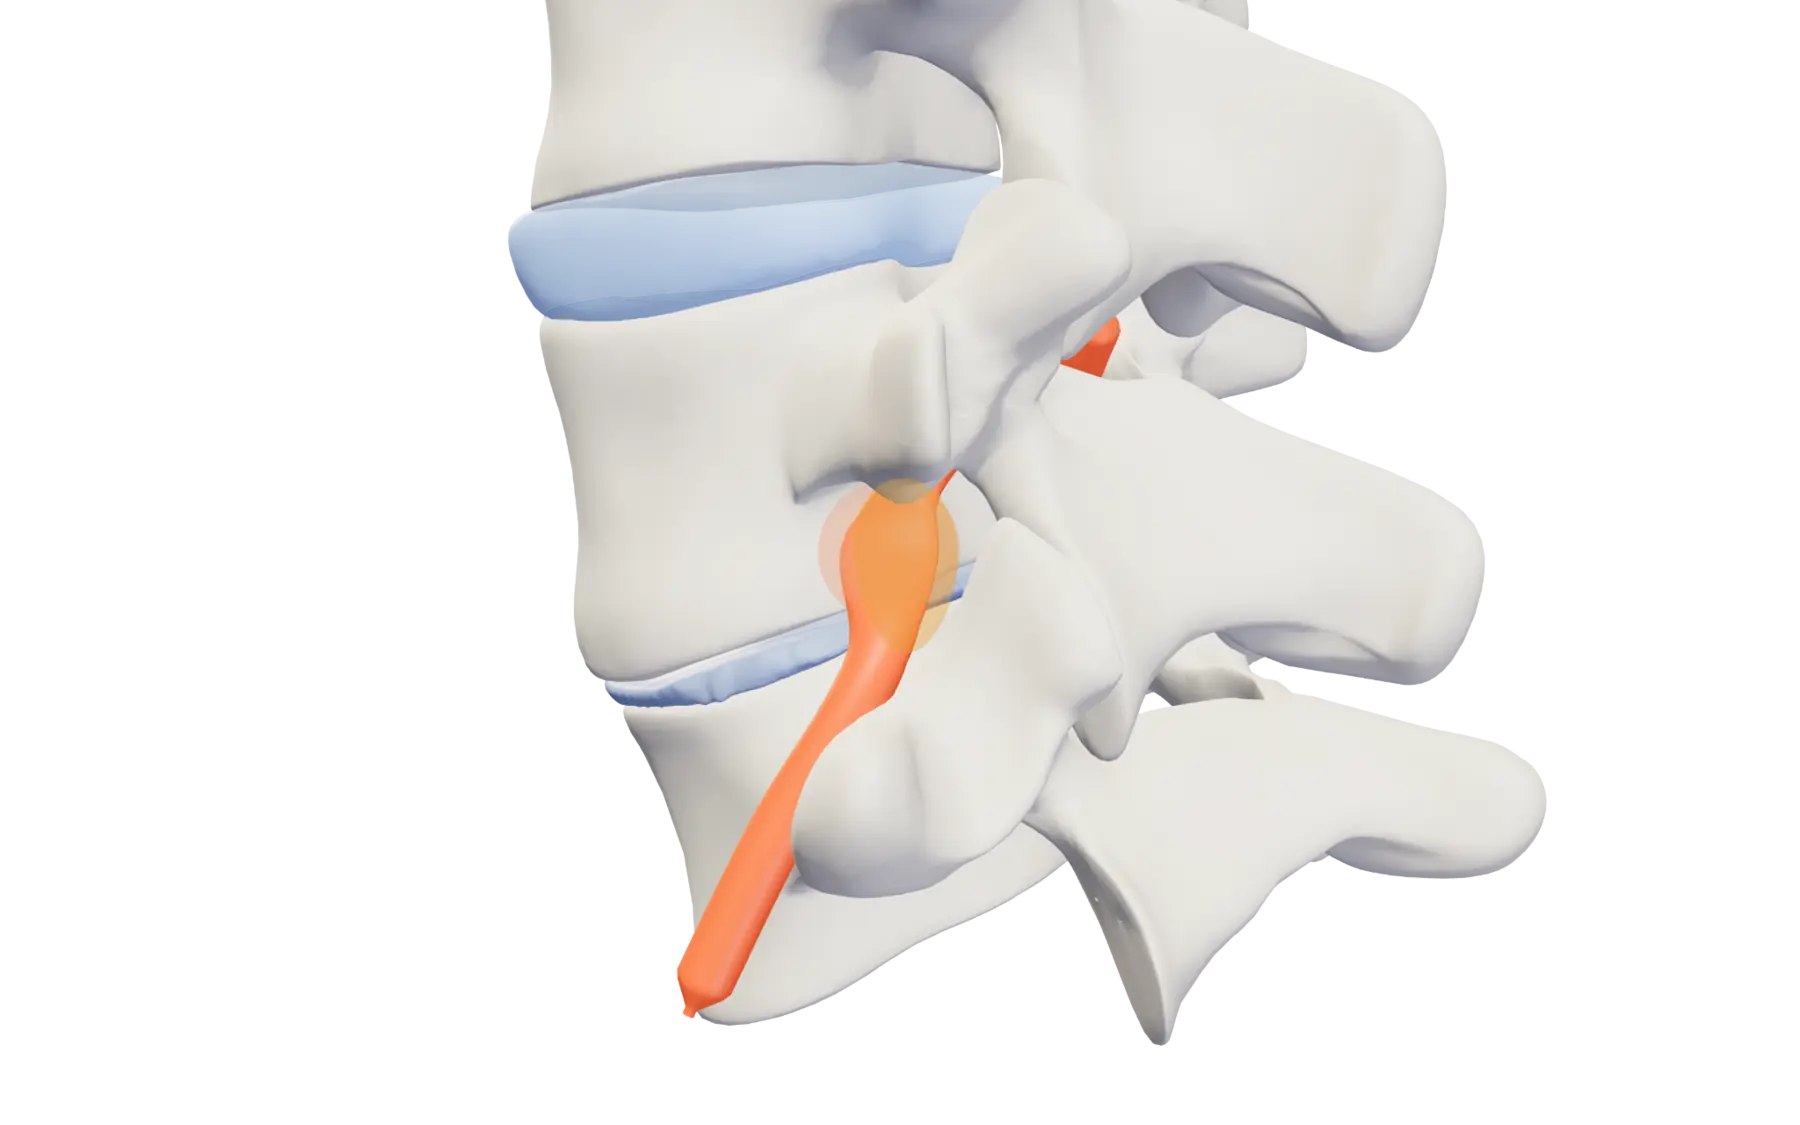 Lost foraminal height
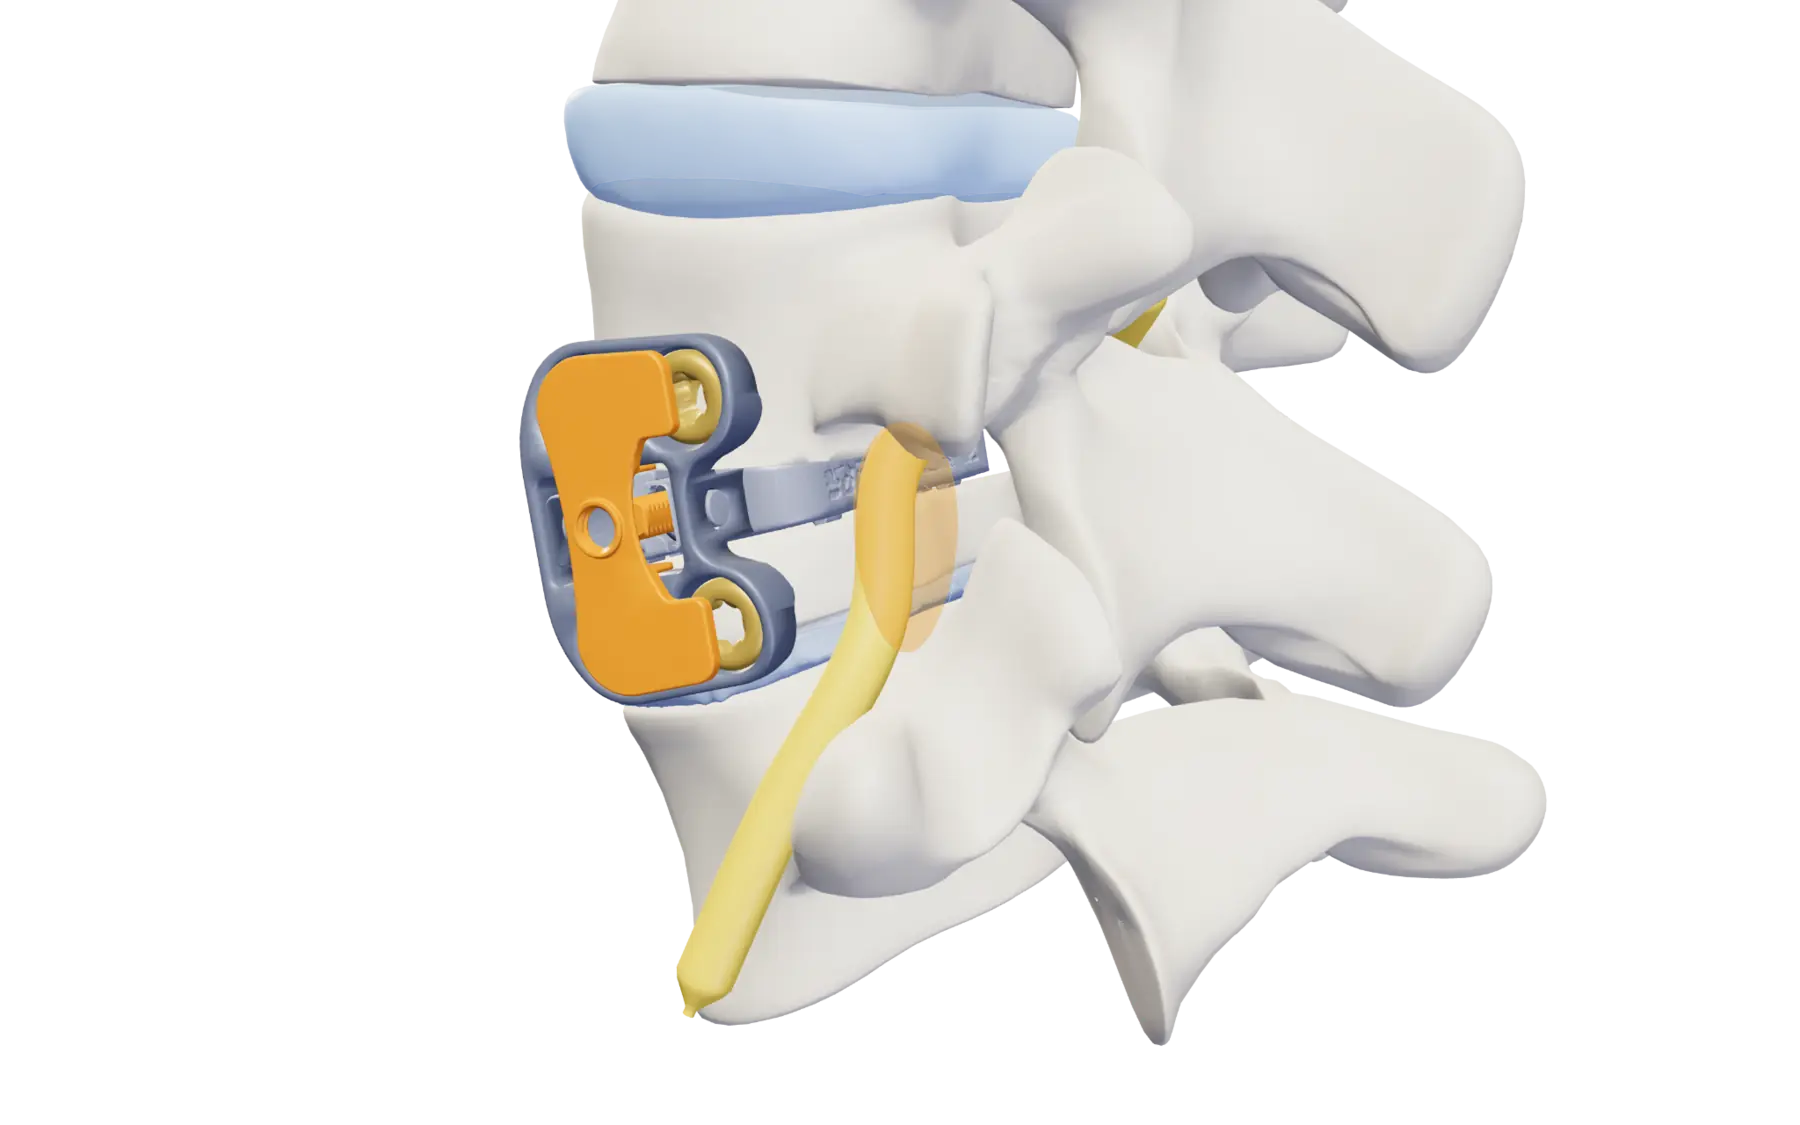 Height restored with VBO
| Feature | Direct decompression | Interbody fusion | VBO |
|---|---|---|---|
| Decompression | Direct | Indirect | Indirect |
| Disc resection | Not typically | Yes | No |
| Restores foraminal height | No | Yes | Yes |
| Alignment options | Not addressed | Lordotic and coronal implants | Lordotic and coronal implants |
| Where bone heals | N/A | Between vertebrae | Within one vertebra |
| Motion across the disc | Preserved | Fused | Designed to be preserved |
Direct decompression includes procedures such as foraminotomy and laminectomy.
Patient selection
VBO offers a motion-preserving option for appropriately selected patients with leg-dominant symptoms associated with vertical foraminal stenosis, when foraminal height restoration and indirect decompression are clinically appropriate.
Define the pathology. Confirm that the exiting nerve root is affected by vertical foraminal narrowing and that indirect decompression is clinically appropriate.
Assess the motion segment. Consider disc condition, instability, deformity, prior treatment, and other anatomy that may favor a different procedure.
Evaluate the full patient. Symptoms, imaging, health, bone quality, goals, and treatment history remain part of the surgeon’s decision.
Follow the cleared labeling. This overview doesn’t replace the Vertiwedge Instructions for Use or clinical judgment.
Technique
VBO is performed through one lateral approach in three phases. Surgeons complete procedure-specific training before their first case, and the Surgical Technique Guide provides full detail.
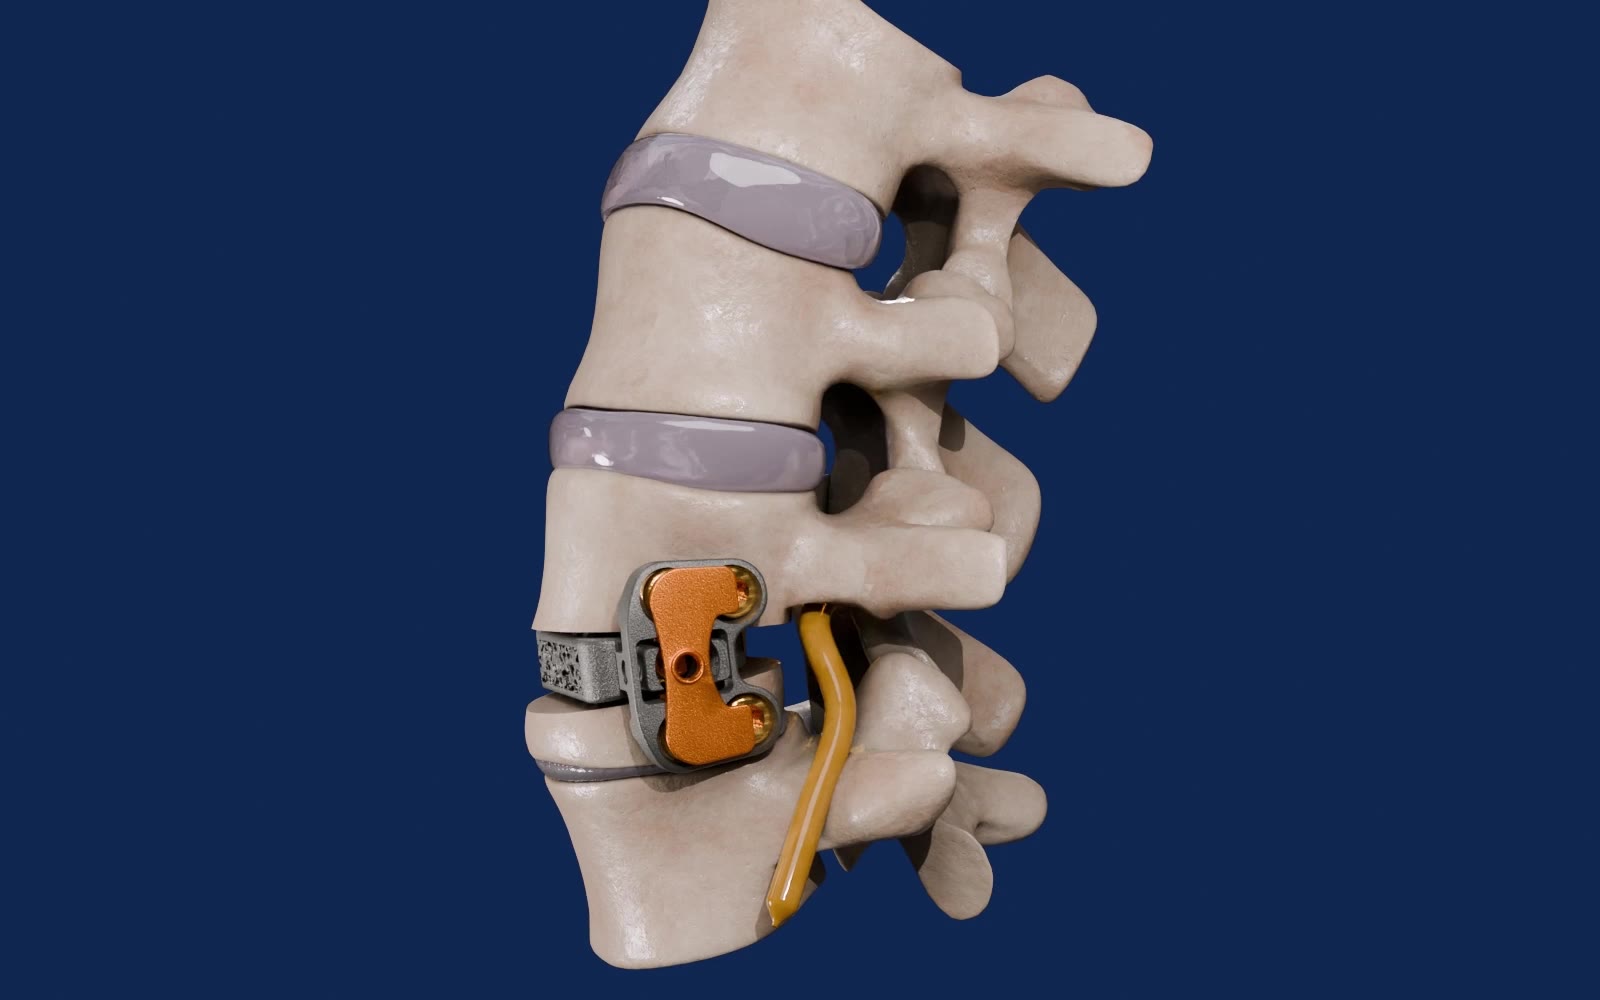
Use a lateral corridor anterior to the psoas, appropriate to the treated level and patient anatomy.
Create the controlled osteotomy within the target vertebral body using dedicated instrumentation.
Use Vertiwedge to restore and support vertebral body height, then deploy the staple to secure the far side; bone screws and the lateral plate secure the near side, all through the same lateral approach.
A proprietary deployable staple mechanism, protected by issued and pending patents, extends, rotates, and retracts to secure the far side of the vertebra.
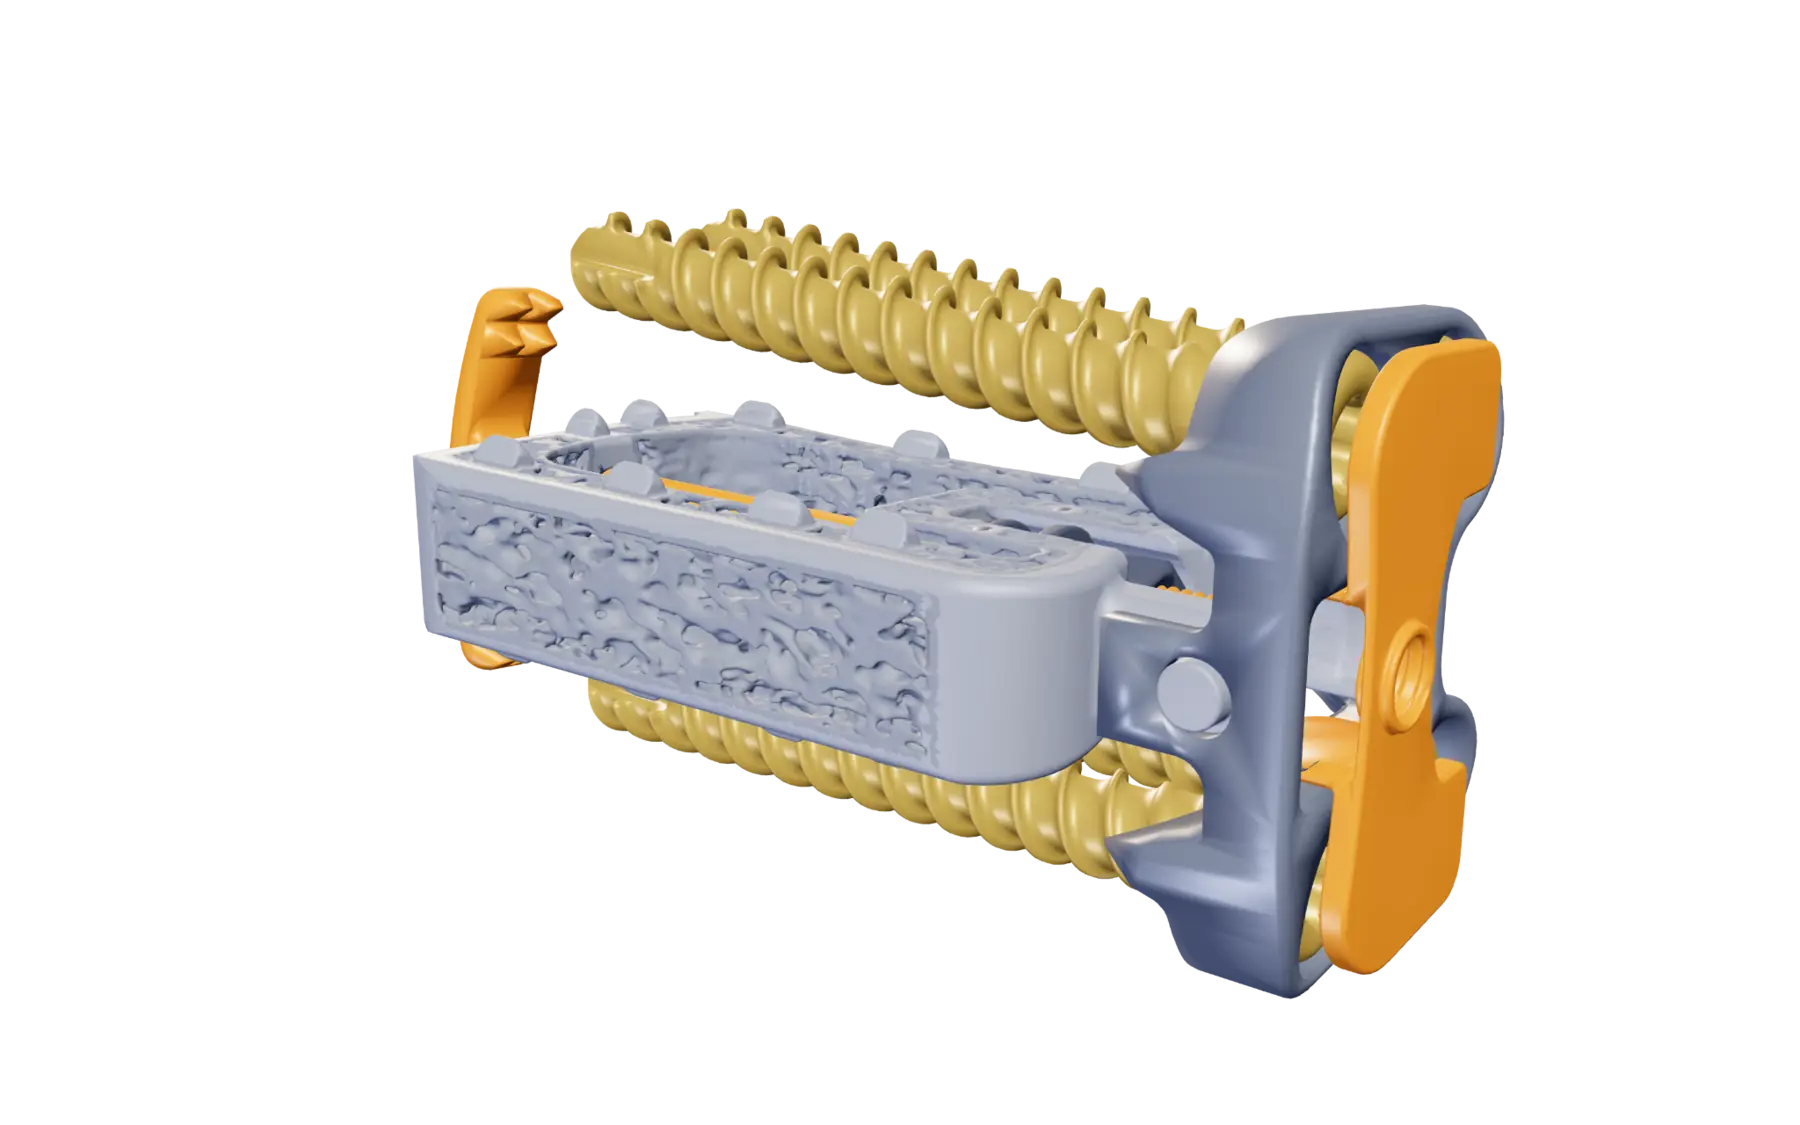
Far-side fixation: the deployable staple.
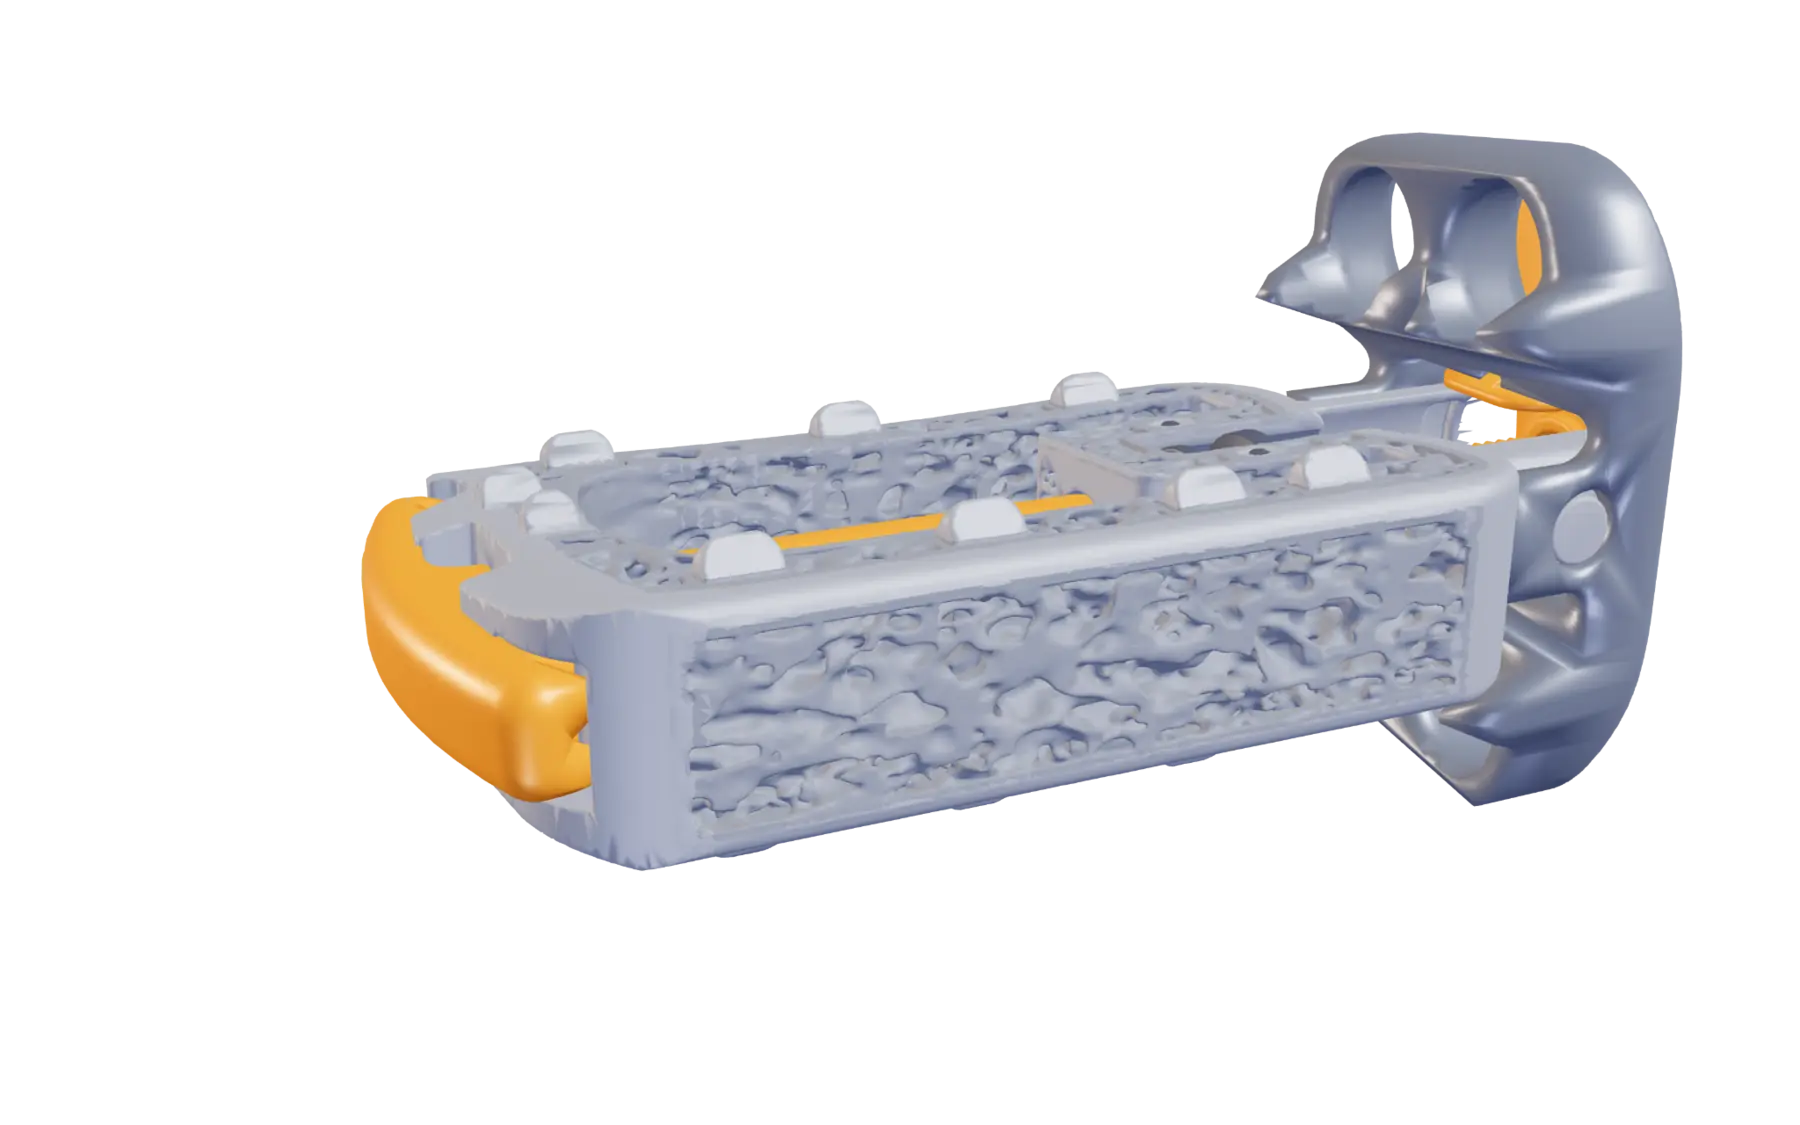
The deployable staple remains housed within the implant during placement.
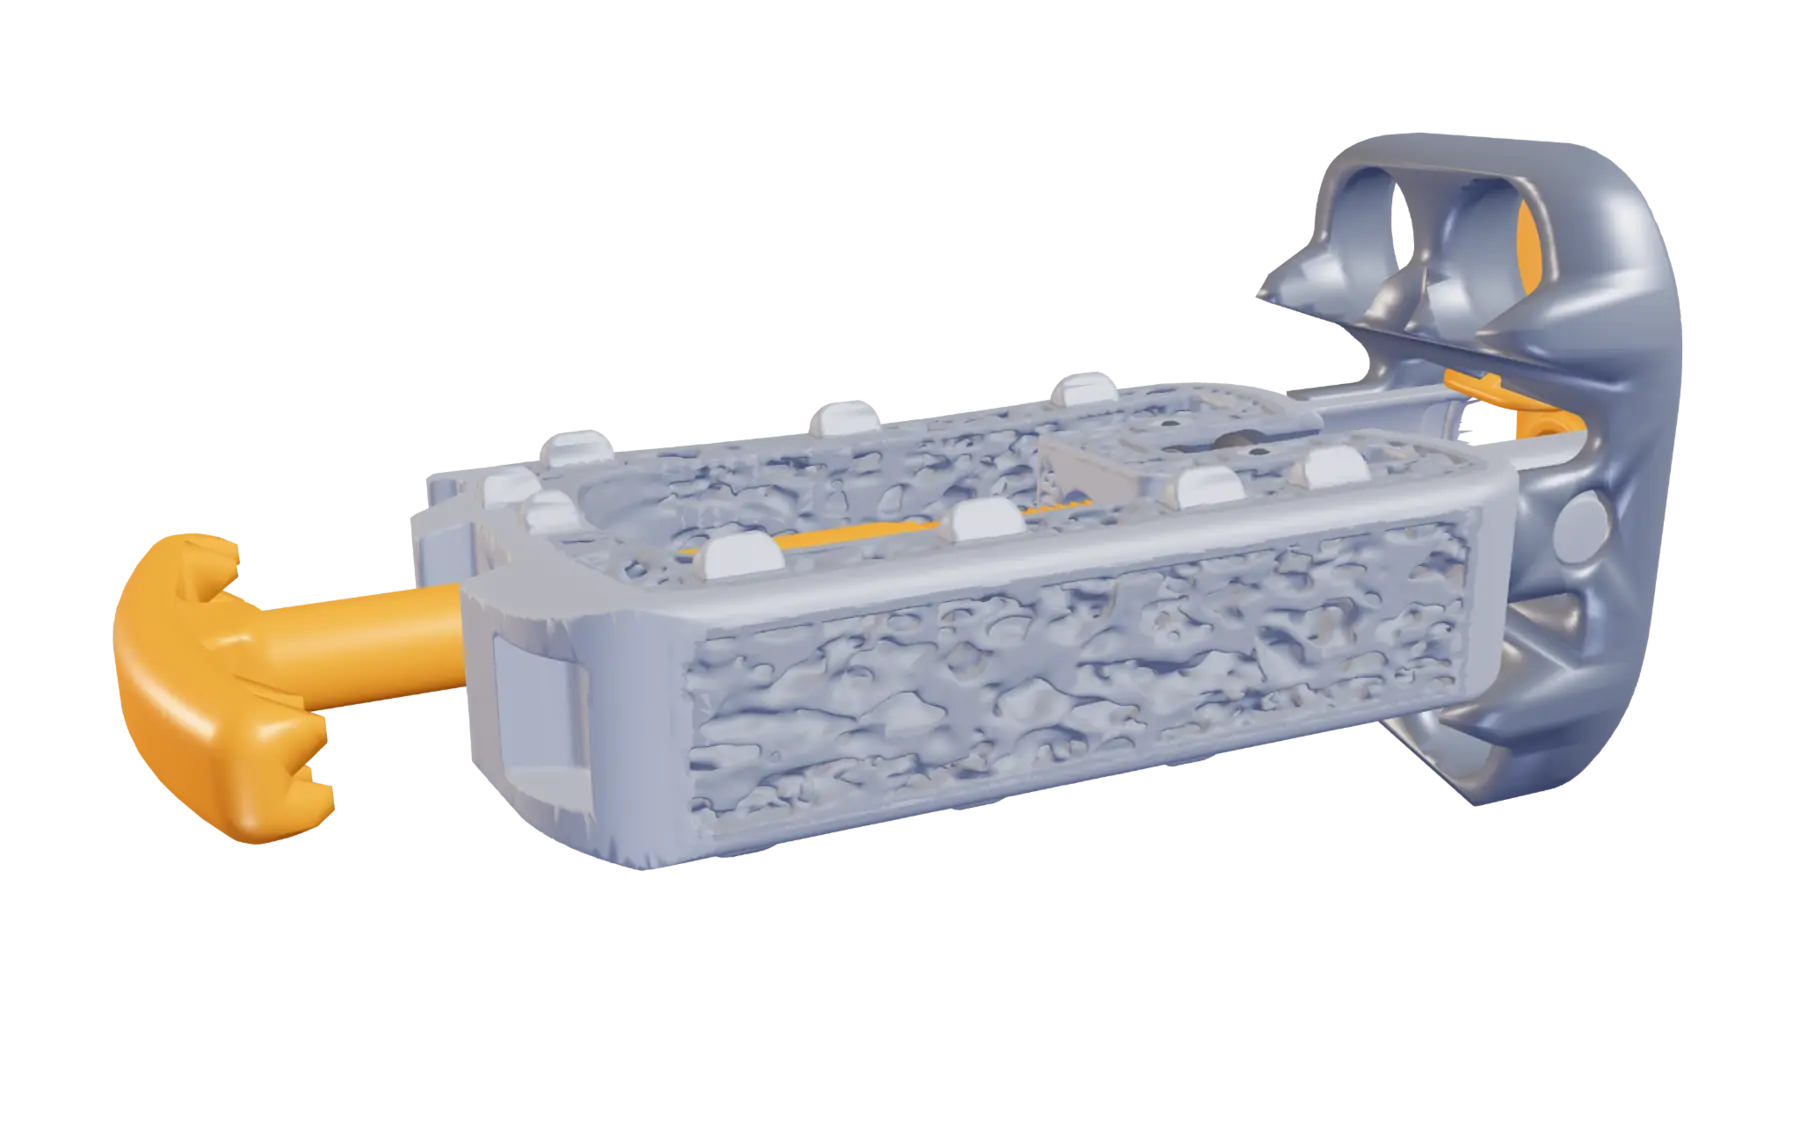
The staple advances across the vertebral body.
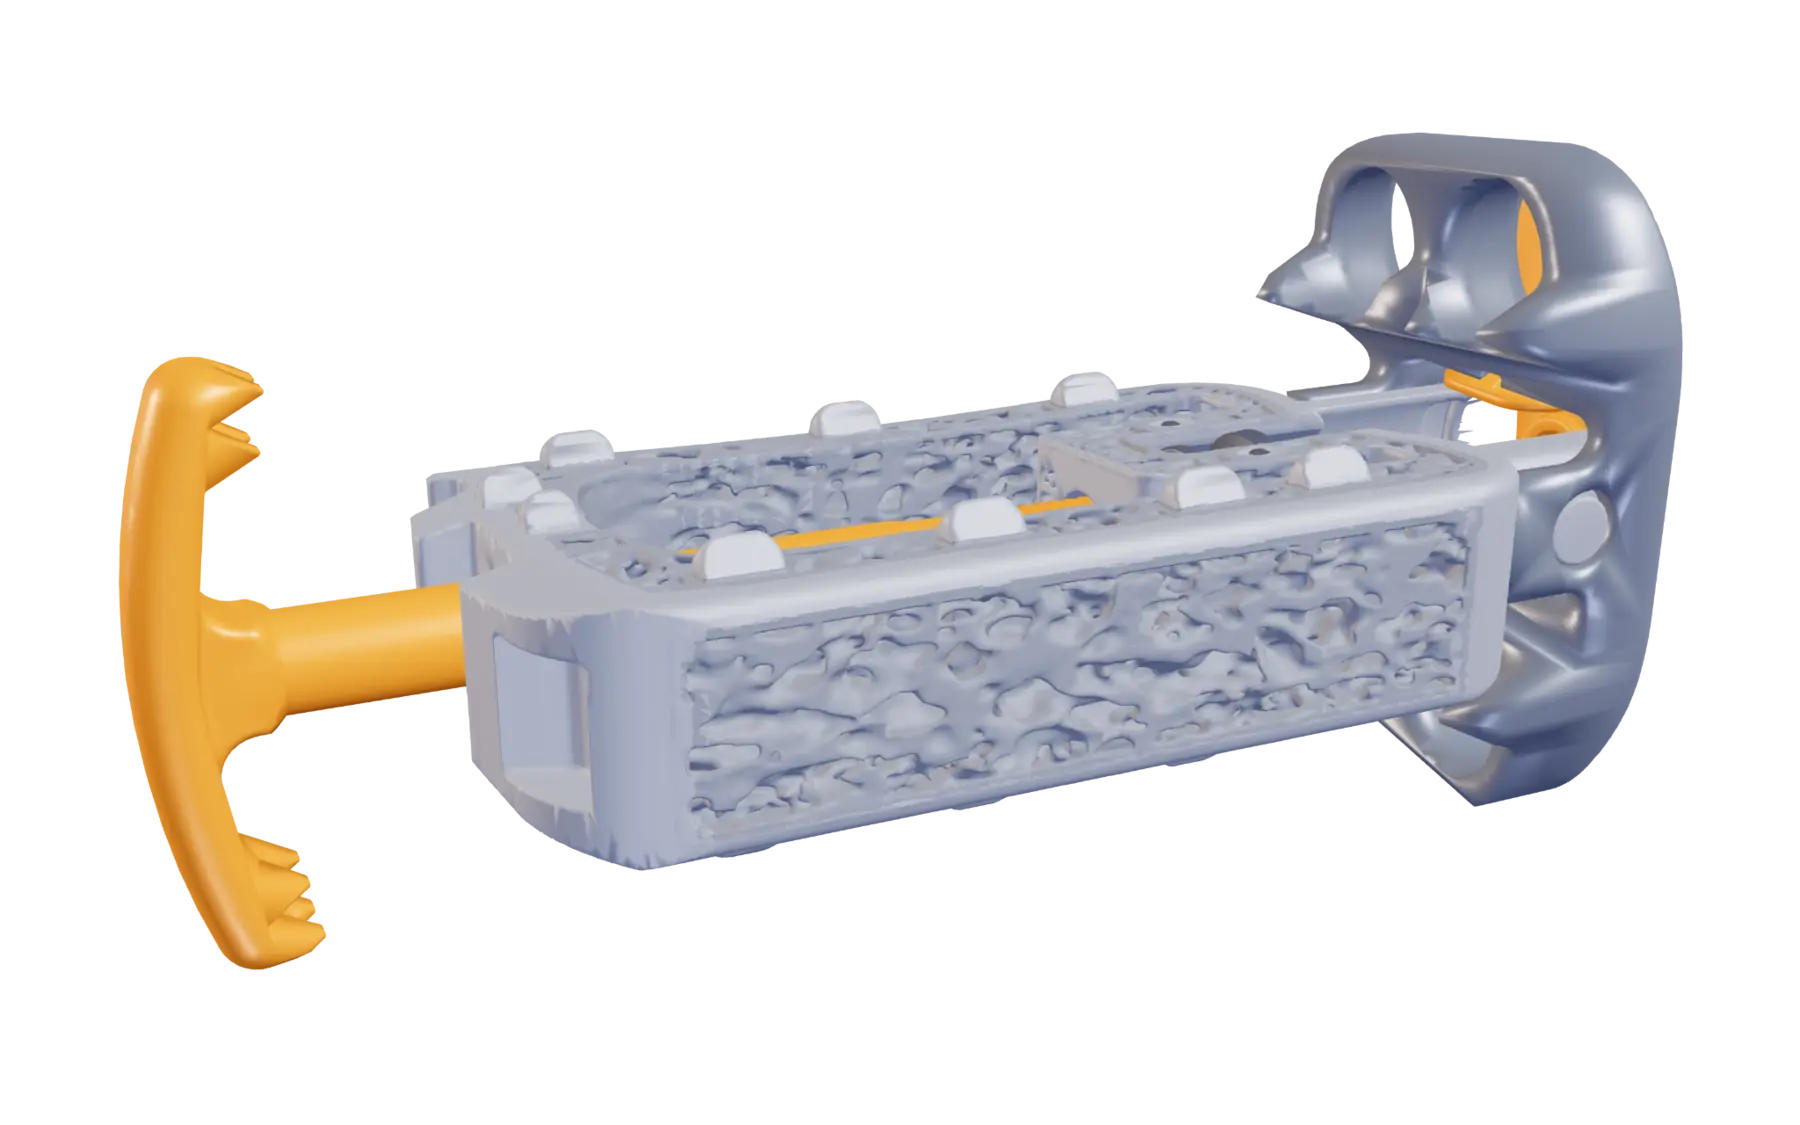
The staple turns into its fixation orientation.
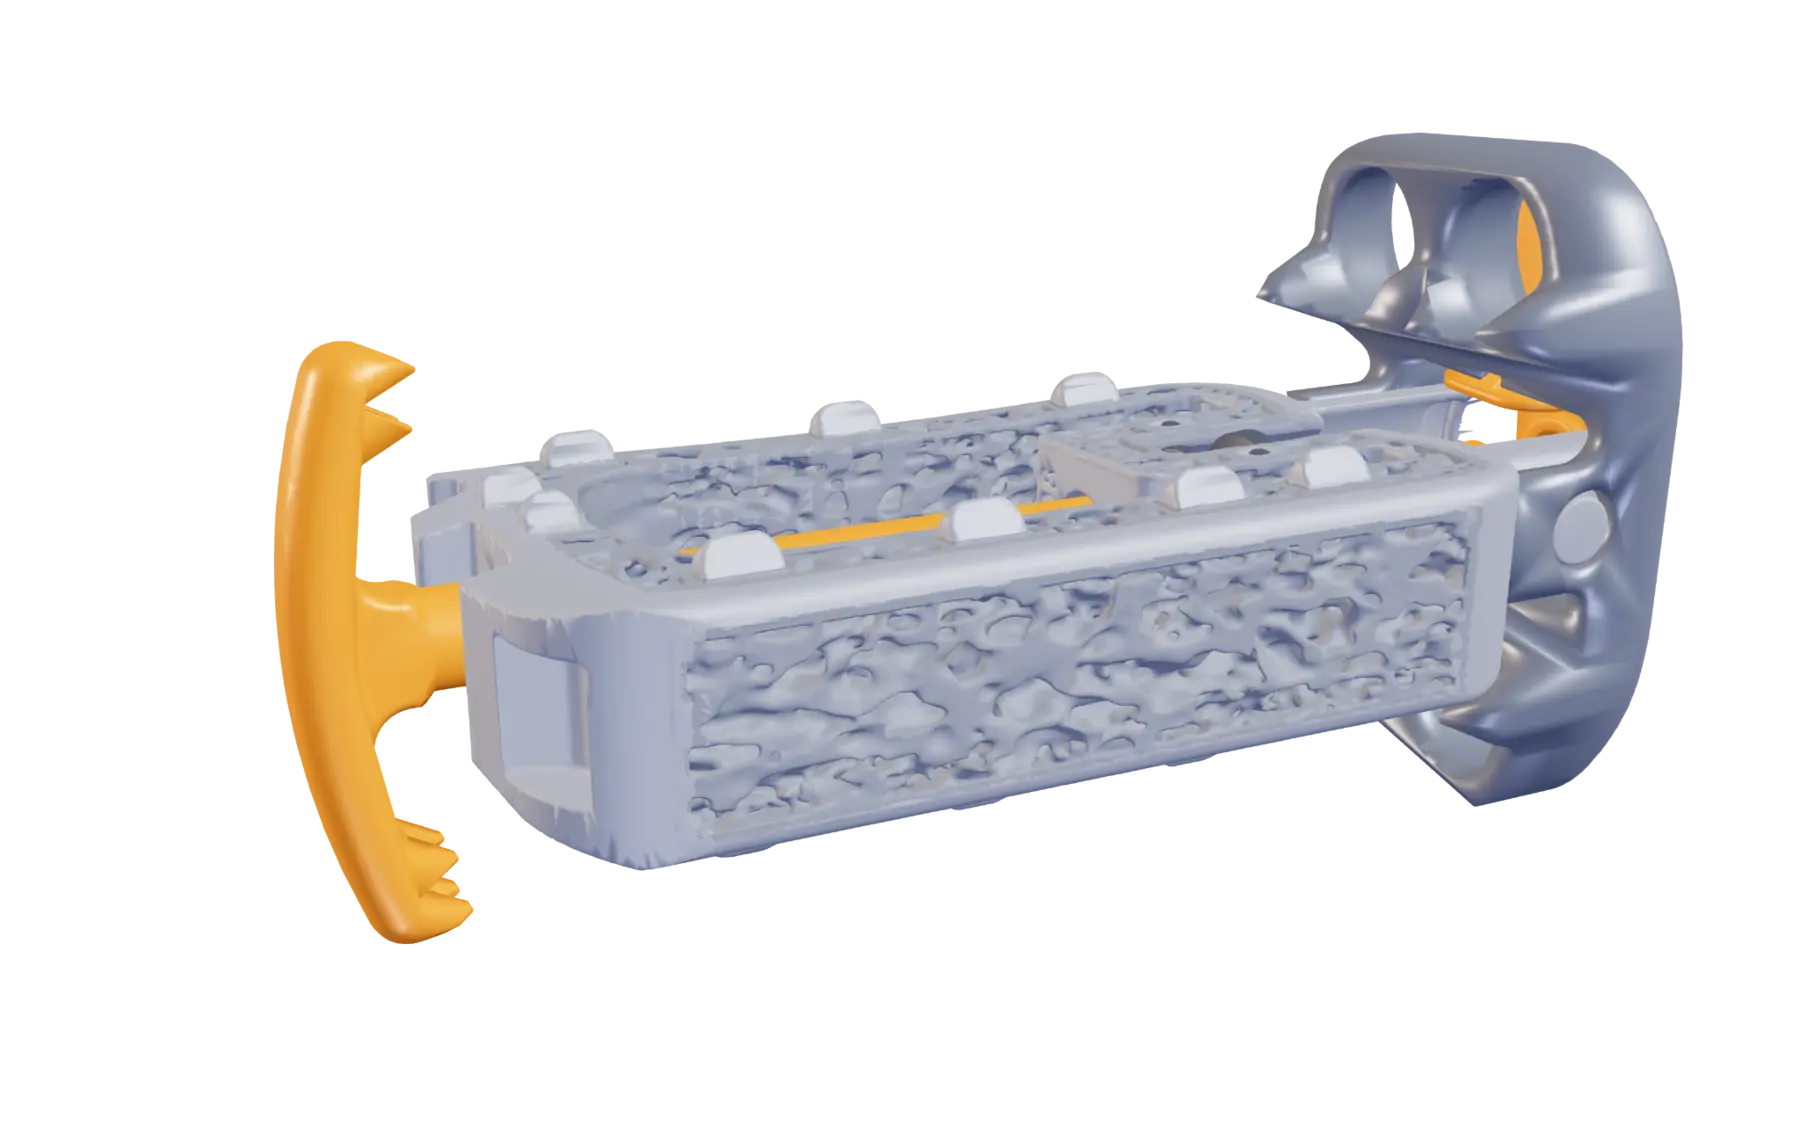
The staple draws into position to secure the far side.
Evidence
Foundation Surgical is building the evidence base for VBO. Regulatory clearance, mechanism, and early clinical observations each answer different questions, and we present them that way.
Refer to the current Vertiwedge labeling and Instructions for Use for indications, contraindications, warnings, and precautions.
View FDA clearance K241468Through an anterior-to-psoas lateral approach, Vertiwedge restores height within the treated vertebra. Bone screws and a lateral plate secure the near side, while the deployable staple secures the far side through the same access.
Imaging showed osseous union across the osteotomy, maintenance of the decompression achieved at surgery, and no evidence of implant subsidence. These findings reflect one patient at one follow-up interval.

From the first case
“For patients with foraminal stenosis, the choice has often been a decompression that doesn’t restore height or a fusion that gives up motion. My first VBO patient didn’t want a fusion and wasn’t going to have one. VBO gave us a way to restore height and decompress the nerve without fusing the disc.”
Shirvinda Wijesekera, MD
Orthopaedic Spine Surgeon, Connecticut Orthopaedics
Coding and reimbursement
Unlike many new spine technologies, VBO is reported using established Category I CPT® codes, so there’s no waiting on a new code. Our coding and reimbursement team supports surgeons, practices, and hospitals with coding questions, documentation, and preauthorization.
Coding information is provided for reference only. Providers are responsible for code selection, and the existence of a code does not guarantee coverage or payment. CPT® is a registered trademark of the American Medical Association.
See VBO in action
Request a guided technical review covering the surgical technique, patient selection, and what it takes to bring VBO to your hospital.
Our technologies
For patients who need an interbody fusion, Interwedge® brings the same proprietary deployable staple mechanism to the disc space. It’s FDA cleared for standalone use.
Explore our products →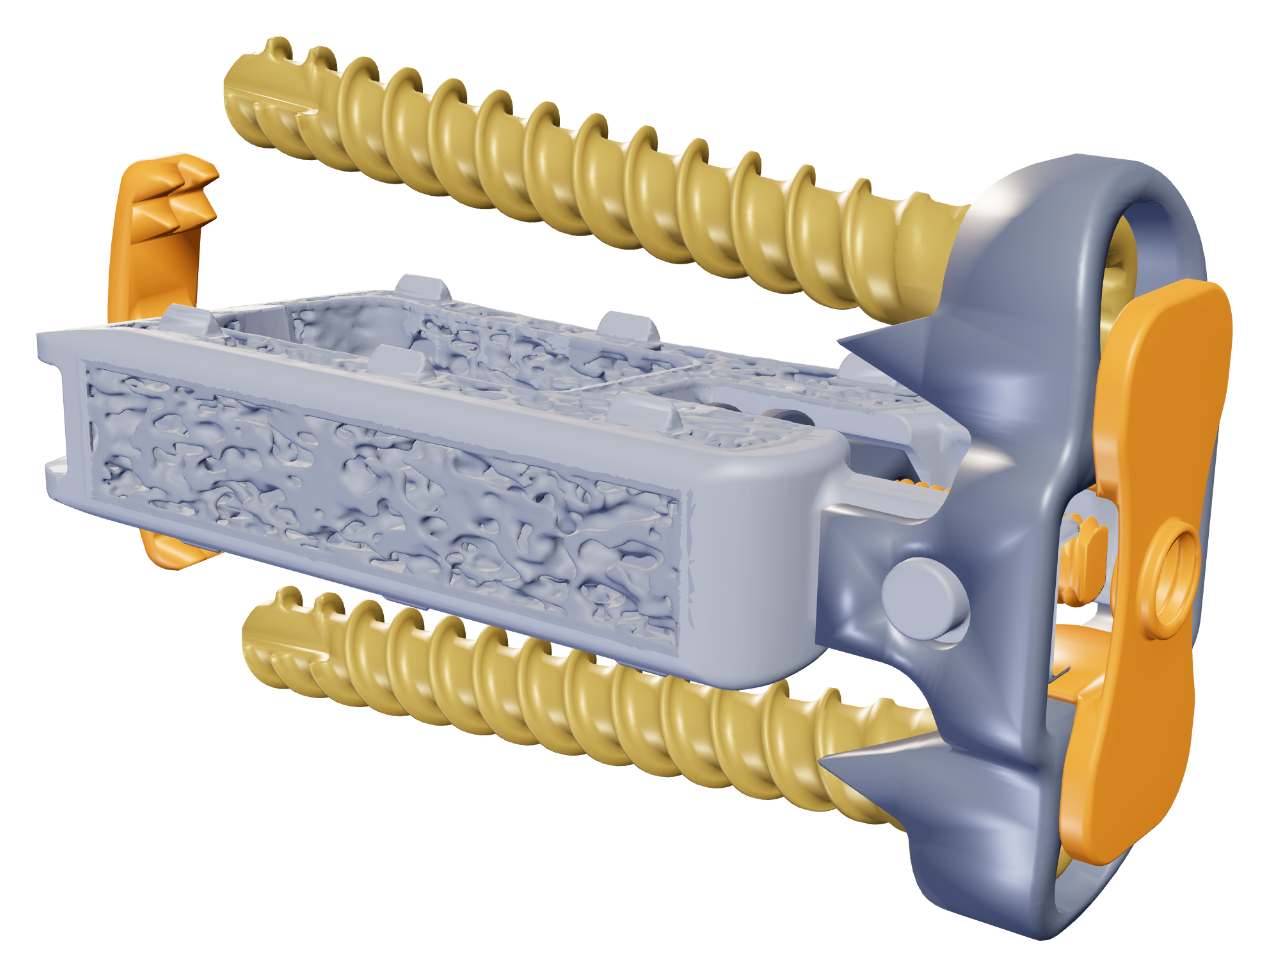
Professional inquiry
Whether you’re a surgeon, hospital, or distribution partner, tell us what you’d like to discuss and the right person will follow up.